Autoimmune diseases can affect the eyes by causing inflammation, dry eyes, optic nerve damage, uveitis, or retinal problems, sometimes before other symptoms appear. Early diagnosis and coordinated care with an ophthalmologist can help protect vision and prevent long-term complications.
Quick Answer: Autoimmune disease can inflame almost any layer of the eye. Episcleritis is usually mild and self-limiting, scleritis is deeper, more painful, and sight-threatening if untreated, uveitis affects the inside of the eye and needs prompt steroid treatment, and Sjogren’s syndrome causes chronic dry eye through damaged tear glands. Anyone on long-term hydroxychloroquine also needs annual retinal screening regardless of symptoms, because toxicity can develop silently.
Autoimmune Disease and Your Eyes: What Rheumatoid Arthritis, Lupus and Sjogren’s Can Do to Your Vision
If you have rheumatoid arthritis, lupus, Sjogren’s syndrome, or another autoimmune condition, your eyes are not a side issue. They are often where the disease shows up first, or where it quietly does the most damage while everyone is focused on joints and skin and bloodwork.
I see this pattern often: a patient on long-term immune therapy who has never had a baseline eye check, or one who assumes a red, painful eye is just dryness when it is actually scleritis. The eye has its own version of almost every autoimmune complication your rheumatologist tracks elsewhere in the body.
In this article, I will cover the five autoimmune eye conditions I see most often: uveitis, episcleritis, scleritis, Sjogren’s-related dry eye, and the retinal toxicity risk from long-term hydroxychloroquine (HCQS) use. I will also flag two related conditions worth knowing about: peripheral ulcerative keratitis and autoimmune optic neuritis.
Dr Shibal Bhartiya is a fellowship-trained glaucoma specialist and Mayo Clinic Research Collaborator with over 25 years of experience. Her approach focuses on identifying risk before damage is irreversible, simplifying treatment decisions, and protecting vision long-term. Emphasis on early detection, risk assessment, and continuity of care. She is rated 5 stars across 1,500+ patient reviews on Google.
Uveitis
Uveitis is inflammation inside the eye, affecting the iris, ciliary body, or choroid. It is one of the most common autoimmune eye complications and can occur with ankylosing spondylitis, juvenile idiopathic arthritis, sarcoidosis, Behcet’s disease, and inflammatory bowel disease, among others.
| Symptom | What It Means | What To Do About It |
| Eye pain with redness, often around the iris | Active inflammation of the front of the eye (anterior uveitis) | See an ophthalmologist within 24 to 48 hours; do not wait this out |
| Sensitivity to light (photophobia) | Inflamed iris muscle spasming in response to light | Dark glasses help short term; this needs treatment, not just avoidance |
| Blurred vision with floaters | Inflammatory cells or debris in the vitreous (posterior or intermediate uveitis) | Needs dilated examination to localise where the inflammation is occurring |
| Recurrent episodes in the same or other eye | Suggests an underlying systemic autoimmune trigger rather than an isolated eye problem | Warrants referral back to rheumatology for systemic work-up if not already diagnosed |
| No pain but gradually worsening vision | Possible chronic or posterior uveitis, which can be painless despite significant inflammation | Do not assume painless means harmless; this still needs urgent assessment |
| Uveitis not responding to first-line steroid drops | May need systemic immunosuppression or a biologic agent | Co-management between ophthalmology and rheumatology is usually required |
Episcleritis
Episcleritis is inflammation of the thin layer just under the conjunctiva. It is usually mild, often recurrent, and frequently mistaken for conjunctivitis.
| Symptom | What It Means | What To Do About It |
| Sudden patch of redness, mild discomfort | Localised inflammation of episcleral vessels, often without a clear trigger | Usually self-limiting; lubricating drops and cold compresses help |
| Redness that blanches when you press gently with a cotton bud | A useful bedside sign distinguishing episcleritis from deeper scleritis | If it blanches, it is reassuring; if it does not, seek same-day assessment |
| Mild tenderness but no severe pain | Episcleritis is typically far less painful than scleritis | Severe pain is a red flag that this may be scleritis instead |
| Recurrent episodes over months or years | Can be idiopathic or linked to mild autoimmune activity | Worth screening for rheumatoid arthritis or other connective tissue disease if recurrent |
| Nodular, raised area of redness | Nodular episcleritis, a slightly more persistent subtype | May need a short course of topical steroid under supervision |
Scleritis
Scleritis is deeper, more severe inflammation of the sclera itself, the white outer wall of the eye. It is strongly associated with rheumatoid arthritis, granulomatosis with polyangiitis, and lupus, and it can threaten vision if untreated.
| Symptom | What It Means | What To Do About It |
| Deep, boring eye pain, often worse at night | Inflammation of the sclera, a much more severe process than episcleritis | Needs same-day ophthalmology assessment; this is not a wait-and-watch condition |
| Pain radiating to the jaw, brow, or face | Scleral pain frequently refers along trigeminal nerve pathways | Do not dismiss as a headache or sinus issue if accompanied by eye redness |
| Redness that does not blanch on pressure | Deeper vessel involvement than episcleritis | Confirms the need for urgent evaluation rather than home care |
| Thinning or a bluish discolouration of the sclera | Sign of necrotising scleritis, a severe and sight-threatening subtype | Requires urgent systemic immunosuppression; same-day specialist referral |
| Scleritis as a first presentation of joint or skin symptoms | The eye can be the first organ to show systemic autoimmune disease | Needs prompt rheumatology referral alongside eye treatment |
| Reduced vision alongside scleral pain | Associated uveitis, glaucoma, or corneal involvement can occur with severe scleritis | Needs full eye examination, not just treatment of the visible redness |
Dry Eye and Sjogren’s Syndrome
Sjogren’s syndrome is an autoimmune condition that attacks the tear and salivary glands directly, producing a more severe and treatment-resistant dry eye than typical age-related dryness.
| Symptom | What It Means | What To Do About It |
| Persistent gritty, burning dryness despite drops | Sjogren’s-related dry eye often does not respond to standard lubricants alone | Needs assessment for Sjogren’s if dryness is disproportionate or progressive |
| Dry mouth alongside dry eyes | Classic combination pointing to Sjogren’s syndrome affecting both gland systems | Worth a blood test panel (anti-Ro/La) and rheumatology referral |
| Recurrent corneal erosions or filaments | Severe tear film instability damaging the corneal surface | May need punctal plugs, serum tears, or scleral lenses, not just drops |
| Dry eye that worsens despite treating typical MGD | Suggests an aqueous-deficient, not just evaporative, dry eye component | Needs Schirmer’s testing and systemic work-up rather than repeating MGD treatment |
| Joint pain, fatigue, or skin dryness alongside eye dryness | Systemic features suggesting Sjogren’s rather than isolated ocular dryness | Refer to rheumatology for formal diagnosis and systemic management |
Hydroxychloroquine (HCQS) Retinal Toxicity
Hydroxychloroquine is a mainstay treatment for lupus, rheumatoid arthritis, and other autoimmune conditions. It is generally safe, but long-term use carries a small, dose-dependent risk of retinal toxicity that is irreversible once it progresses, which is why screening matters even without symptoms.
| Symptom | What It Means | What To Do About It |
| No symptoms at all, but on HCQS for more than 5 years | Toxicity is often silent in early stages and detected only on screening | Annual screening is required regardless of symptoms after 5 years of use |
| Difficulty reading or patchy missing areas in central vision | Possible bull’s eye maculopathy from established toxicity | Needs urgent retinal evaluation and discussion with rheumatology about dosing |
| High daily dose relative to body weight | Risk rises above 5 mg/kg/day of real body weight | Confirm dosing with your rheumatologist; weight-based dosing reduces risk |
| Pre-existing kidney disease or retinal disease | Both increase toxicity risk independent of dose or duration | Flag these conditions before starting HCQS so screening starts earlier |
| Annual screening showing early paracentral changes on OCT or visual fields | Early, often asymptomatic, sign of toxicity preceding visible vision loss | Usually prompts a dose reduction or drug change in consultation with rheumatology |
Important: Screening for HCQS toxicity should start at baseline before treatment begins, then annually after 5 years of use, sooner if risk factors like high dose, kidney disease, or pre-existing retinal disease are present. This typically includes OCT, visual fields, and sometimes multifocal ERG or fundus autofluorescence.
Two More Worth Knowing About
Peripheral Ulcerative Keratitis (PUK)
PUK is a crescent-shaped thinning and ulceration at the edge of the cornea, strongly linked to rheumatoid arthritis and granulomatosis with polyangiitis. It can progress to corneal perforation if untreated and is considered an ophthalmic emergency.
Autoimmune Optic Neuritis
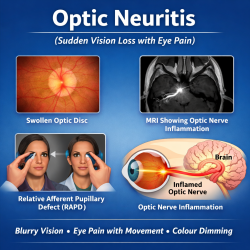
Optic neuritis, inflammation of the optic nerve causing pain on eye movement and vision loss, can occur in multiple sclerosis, neuromyelitis optica, and MOG antibody disease. It needs urgent neuro-ophthalmic assessment, since the underlying diagnosis changes the treatment significantly.
When To See a Doctor
- Eye pain that wakes you at night or is described as deep and boring, not surface irritation
- Redness that does not blanch when you press a cotton bud gently against it
- Any vision change, however mild, alongside eye redness or pain
- Dry eye symptoms that do not improve with standard lubricants after a few weeks
- Known autoimmune disease with a new eye symptom of any kind
- Long-term hydroxychloroquine use without an annual eye screening on record
- Eye symptoms appearing before any formal autoimmune diagnosis has been made
What This Means for You
If you have an autoimmune condition, your eye care should not be separate from your rheumatology care. The two specialties need to talk to each other, especially around long-term medications like hydroxychloroquine and around any new eye symptom that could signal a flare. An annual baseline eye check, even with no symptoms, catches problems like HCQS toxicity and early scleritis before they cause permanent damage.
This article is part of the Dry Eye Hub. Please also read Basics of Dry Eye, Dry Eye Second Opinion and Dry Eye: A Chronic Disease. Why Vision Becomes Blurred After Reading or Screen Use, and Why Are Your Dry Eye Drops Not Working may also help you understand your problem better.
This page is also a part of the Neuro-Ophthalmology hub. Read about our full approach to neurological vision conditions, Some vision problems are not eye problems, and about optic nerve disease.
If you are weighing a second opinion on an autoimmune eye diagnosis, our Second Opinion Page outlines how that process works.
Frequently Asked Questions
Can autoimmune eye disease occur before other symptoms appear?
Yes. Uveitis, scleritis, and even dry eye can be the first sign of an underlying autoimmune condition, sometimes appearing years before joint or skin symptoms develop. This is one reason ophthalmologists often refer patients to rheumatology rather than the other way round.
Is hydroxychloroquine safe for long-term use?
Yes, for most people, but it requires monitoring. The risk of retinal toxicity is low at recommended doses but rises with duration of use, higher doses, and certain risk factors like kidney disease. Annual screening after 5 years of use is the standard of care, not an optional extra.
How do I tell episcleritis apart from scleritis at home?
Episcleritis usually blanches, turns paler, when you press a clean cotton bud gently against the white of the eye, and the pain is mild. Scleritis does not blanch and causes deep, often severe pain. If you are unsure, treat it as scleritis until an ophthalmologist tells you otherwise.
Why does Sjogren’s dry eye not respond to normal eye drops?
Sjogren’s syndrome damages the tear-producing glands directly, reducing the volume of tears your eye can make rather than just affecting tear quality. Standard lubricating drops can help but often are not enough on their own, which is why options like punctal plugs or serum tears are considered.
Does treating the autoimmune disease also treat the eye problem?
Often yes, particularly for uveitis and scleritis, where systemic immunosuppression treats both the eye and the underlying disease together. However, some eye complications, like HCQS toxicity or Sjogren’s dry eye, need their own dedicated monitoring and treatment regardless of how well the systemic disease is controlled.
Key Takeaways
- Autoimmune disease can affect nearly every layer of the eye, from the surface to the optic nerve
- Episcleritis is usually mild; scleritis is deep, painful, and sight-threatening if untreated
- Uveitis needs prompt treatment even when painless, since delayed care risks permanent vision loss
- Sjogren’s dry eye often needs more than standard lubricants
- Anyone on long-term hydroxychloroquine needs annual retinal screening, with or without symptoms
- Eye symptoms can be the first sign of autoimmune disease, before a formal diagnosis exists
Book a Consultation
If you have an autoimmune condition and have not had a baseline eye examination, or if you are on long-term hydroxychloroquine without a recent screening, it is worth getting this checked before symptoms appear. Early detection is what makes the difference between a manageable finding and irreversible vision loss in these conditions.
[Book an Appointment → contact us]
About the Author
This article was written by Dr Shibal Bhartiya, fellowship-trained glaucoma specialist and Mayo Clinic Research Collaborator, Clinical Director at Marengo Asia Hospitals, Gurugram, known for ethical, patient-centred glaucoma care and independent glaucoma second opinions. She is also the Program Director for Community Outreach & Wellness; and for the Marengo Asia International Institute of Neuro and Spine.
She has published peer-reviewed research on glaucoma management, examining how treatment decisions should balance medical evidence, patient preferences, and long-term vision outcomes.
As Editor-in-Chief of Clinical and Experimental Vision and Eye Research and Executive Editor of the Journal of Current Glaucoma Practice (Pubmed Indexed, official journal of the International Society of Glaucoma Surgery), Dr Shibal Bhartiya brings editorial and research depth to every clinical decision. Her 200+ publications, including 90+ PubMed-indexed publications and 28 edited textbooks span glaucoma biology, surgical outcomes, health equity, and emerging diagnostics.
1500+ Five Star Patient Reviews Google Business Profile
If you are unable to come to Dr Bhartiya’s clinic: Read more about teleconsultation
Read her research on PubMed | Google Scholar | ResearchGate | ORCID
Upload your reports for a structured review.| www.drshibalbhartiya.com | +91 88826 38735
Leave a review on Google